
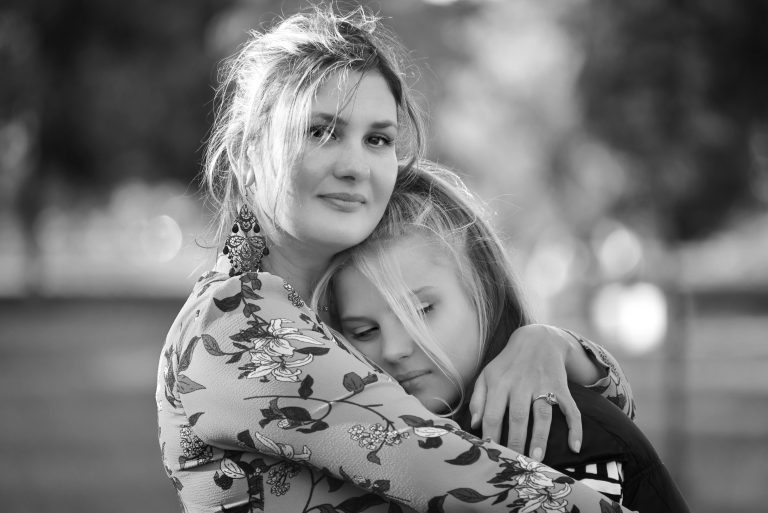
A Patient’s Story
Author: Dr. Virginia de la Lastra
Nancy practices what she will say in the car. She practices it again in the waiting room. Her hands hold restlessly a folder that has grown soft at the corners from being carried. Inside it are years of her daughter’s life, translated into lab sheets and referral notes and the instructions from so many people who were sure they understood. She knows the folder by heart. She has read it over and over, as if she were about to take a final exam she is sure she will fail anyway, but still, looking for the line she could have missed.
Beside her sits her daughter Ellie, her knees together and her sneakers, worn at the heel, because Ellie runs, Ellie swims, Ellie moves, tucked under the chair. She is fourteen. She sits reading a book with the particular stillness of a girl who has learned that invisibility is safe, wearing her oversized black sweatshirt to try to look slimmer. At school this week, someone said something. Nancy doesn’t know exactly what. She only knows that Ellie came home and went straight to her room, and that the light under the door stayed on for a long time.
When the doctor calls their name, Nancy stands up too quickly. The first thing she does is apologize. “I know how this looks,” she says. “I want you to know we’ve tried everything. She eats well. I make sure of it. She is active, she does sports three times a week, she loves to move.”
The doctor doesn’t write anything down. She just listens.
So Nancy keeps going, because the silence needs filling. “It’s not —” and her voice trembles a bit, “— it’s not that we haven’t tried.” She tells the doctor about the pediatrician, who weighed Ellie and looked at Nancy over the top of his glasses and asked what she was feeding her. She tells her about the nutritionist, and the second nutritionist, and the plan, and the other plan. She tells her about the endocrinologist who ordered tests and then called them normal and sent them home with a printed sheet about portion sizes.
She does not tell the doctor about her mother-in-law at Sunday lunch, watching Ellie’s plate. She does not tell her about the words that get said in a family when a child’s body becomes a referendum on the mother. She does not have to. It is all there in the way she holds the folder against her chest, like something that might be taken from her, or like armor.
“They keep telling me the same thing,” Nancy says finally. “That if I just… that it’s about discipline. That a good mother would have fixed this by now.”
While the doctor examines Ellie, asking her about her cycles, which are irregular; about her skin; about how she sleeps; about the fatigue that Ellie mentions almost as an afterthought, the way you mention weather, Nancy opens the folder.
She has one thing she wants the doctor to see. A blood test from eighteen months ago. She slides it across the desk and points to a number, halfway down, that she has looked at a hundred times without understanding.
Fasting insulin: 38 µIU/mL.
“Someone told me this was fine,” Nancy says. “They said it was normal to have higher insulin in puberty.”
The doctor goes quiet in a different way now. Not the listening quiet from before. A quiet that has weight.
Because a healthy fasting insulin in a girl Ellie’s age should be under 10 µIU/mL, not thirty-eight. A fasting insulin this high is a body straining, a pancreas shouting into a room where no one is listening. It is a number that explains things.
It explains why Ellie gains weight from almost nothing, why the exercise and the careful meals never balanced the equation, why a girl who does everything right keeps getting a body that looks, to strangers, like a girl and a mother who do everything wrong. Insulin is the hormone that tells the body to store. When it runs this high, this constantly, the body stores. Not because of weakness. Not because of a plate at Sunday lunch. Because of chemistry.
Someone had held this number in their hands and called it normal. And they had sent this mother home to keep believing the problem was her, and her daughter.
The doctor turns to Nancy and says: “This was never your fault. There is something real happening in Ellie’s body, and it has a name, and we can treat it.”
For a moment Nancy does not react at all. The words seem to reach her from a distance, the way sound arrives late across a valley.
And then something in her face comes apart. Tears start raining down her face. She apologizes for them, of course she does, but she cannot stop. She cries the way people cry when a weight they have carried for so long that they forgot it was a weight is suddenly lifted, and then she cries harder, because even now, even here, her first instinct is to say sorry.
Ellie watches her mother with wide eyes. She has perhaps never seen this. Girls do not always know the weight their parents carry on their behalf.
“You’re telling me,” Nancy manages, “that this isn’t… That I didn’t …”
“You didn’t,” the doctor says. “You’ve been fighting for her this whole time. No one ever told you what you were fighting.”
Here is what Ellie was fighting.
Hormonal Causes of Irregular Periods in Teenagers
For decades, medicine looked at girls like Ellie and saw a behavior problem. Too much of this, not enough of that. The prescription was always some version of try harder, eat less, move more, and beneath it, unspoken, and if it isn’t working, look to the mother.
When we study girls and women aged twelve to thirty-five with ovulatory dysfunction, we see something different. They all come to us with the same kind of problem Ellie had, cycles that would not settle into a rhythm. And every one of them is at least two years past her first period, long enough that “she’s still maturing” is no longer a good enough answer.
Beyond the ovaries, we look at four hormone systems that quietly govern a young woman’s reproductive and metabolic balance: prolactin, androgens, insulin, and the thyroid. We think of these four together as a kind of dashboard. When a cycle goes off track, one of these lights is usually on.
What surprised us was not that the lights were on. It was when. These problems start early. Whatever we find in the grown women, we find already present in the teenagers and at almost the same rates. The hormonal disturbances behind irregular cycles do not arrive at twenty-five or thirty. They are there already at fourteen, at fifteen, at sixteen, often in the very first years a girl’s body begins to speak.
Insulin, the hormone at the center of Ellie’s story, is actually more common in teenagers than in adults. More than half of the adolescents with ovulatory dysfunction we test show signs that their bodies are struggling to manage insulin properly. More than half. This is the hormone that tells the body to store rather than burn, and when it runs high and unheard, weight climbs in ways that no amount of “eat less, move more” can explain. These are girls being blamed for a hormonal pattern no one has measured.
Beyond Insulin: Other Hormones at Play
But insulin is not the whole story, and this is the point. Some girls have excess androgens, the hormones behind acne and unwanted hair, present in about half of both the teenagers and the adults. Some have elevated prolactin, about one in eight. A smaller number have a struggling thyroid. The cause is different from girl to girl, which is exactly why asking only about diet, or glancing at a single number, misses so many of them. We must look at all four systems, at minimum. A blood test waved through as “normal” is how a girl loses years.
And these disturbances rarely travel alone. High insulin drives androgens up by pushing the ovary to make more, and by freeing up the testosterone already there. And the two feed each other, so a small imbalance rarely stays small. It becomes a loop, and the loop tightens with time. This is how a manageable problem at fourteen becomes a much harder one at thirty.
Why Early Diagnosis of Hormonal Imbalances Matters
Treating early can change the whole course of a girl’s life. Caught at fourteen, the imbalance can often be corrected with small adjustments. Once equilibrium is restored, a healthy lifestyle can finally do its work, the way it never could before. These girls had been running the same race as their peers while carrying a weight no one could see, and being measured by the same stopwatch. Treat what was actually wrong, and they respond like any girl would. The oversized black sweatshirt can come off. But the same girl found at thirty-four, after a decade of compounding struggle, is often already carrying what those years cost her: higher cardiovascular risk, infertility, obesity, diabetes, and the quiet toll on her mental health. Not because she failed, because the diagnosis was late.
A healthy ovulatory cycle is one of the clearest signs that a young woman’s whole body is in balance. Ellie’s body was never misbehaving. It was reporting.
It was never Nancy’s fault. It was never Ellie’s. The problem was always something real, and real things can be found.
The answer is almost always there, waiting in a number someone glanced past, in a question no one thought to ask. What is found can be treated. What is caught early can be changed. A whole life can turn on a single act of looking.
Ellie´s condition was found. Not because her body was different from all the others, but because someone finally chose to look.
Somewhere another mother sits in another waiting room, holding her folder against her chest, rehearsing an apology she should never have to make. She does not need to be told to try harder. She needs someone who can see.





